

Vol. 12. Núm. 70.
Páginas 4075-4084 (Enero 2019)

Actualización
Enfermedades cerebrovasculares. Hemorragia cerebral

Cerebrovascular disorders. Brain hemorrhage

P. Irimia SieiraI. EsparragosaR. ValentíE. Martínez-Vila
Doi : https://10.1016/j.med.2019.01.001
Opciones
Resumen

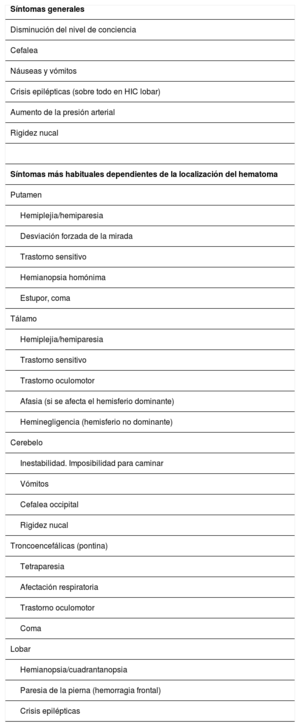
La hemorragia intracerebral (HIC) representa un 20% de todos los ictus, y se produce por la extravasación de sangre dentro del parénquima encefálico, producida por la ruptura de un vaso sanguíneo. Las causas más frecuentes son las denominadas primarias, en las que la pared de los vasos se debilita por la hipertensión art erial crónica o por causas degenerativas como la angiopatía amiloide. Las causas secundarias incluyen las malformaciones vasculares, tumores o hemorragias inducidas por fármacos y drogas de abuso. Los factores de riesgo más relevantes para padecer una HIC son hipertensión arterial, tabaquismo y consumo excesivo de alcohol y drogas. Las manifestaciones clínicas de la HIC están en función de la localización del sangrado y del volumen del hematoma. El diagnóstico requiere la realización de una TC o RM cerebral para distinguir la HIC de una lesión isquémica u otras lesiones estructurales. La localización del sangrado y la presencia de microhemorragias (solo visibles en RM) permiten establecer la causa más probable del sangrado. Estos pacientes deben ser atendidos en un hospital con unidad de ictus y su tratamiento es médico, limitándose la cirugía a un reducido y seleccionado número de casos.

Palabras clave
Hemorragia intracerebral
Diagnóstico
Tratamiento
Abstract

Intracerebral hemorrhage (ICH) accounts for 20% of all strokes; caused by the collection of blood within the cerebral parenchyma as the result of vascular rupture. Taking into account its etiology, primary hemorrhages are the most common and are caused by the vascular wall weakness as a result of chronic arterial hypertension or due to degenerative processes as amyloid angiopathy. Secondary causes include arteriovenous malformations, tumors, hemorrhages induced by drugs and substance abuse. The most important risk factors for developing ICH are arterial hypertension, smoking, substance abuse (alcohol and drugs). Hemorrhage location and bleeding volume determine clinical manifestations. In order to distinguish between ICH and other ischemic or structural lesions, both computed tomography (CT) and magnetic resonance imaging (MRI) may be used for the diagnosis. To determine the most likely bleed cause, bleed location and microbleed detection (only detected by MRI) are necessary. Treatment for patients with ICH is fundamentally medical, and they must be cared for in a hospital with stroke unit. Surgical treatment is only recommended for a reduced number of carefully selected cases.

Keywords
Intracerebral hemorrhage
Diagnosis
Treatment

Identifíquese

¿Aún no es suscriptor de la revista?

Comprar el acceso al artículo

Comprando el artículo el pdf del mismo podrá ser descargado

Teléfono para incidencias

De lunes a viernes de 9h a 18h (GMT+1) excepto los meses de julio y agosto que será de 9 a 15h

Llamadas desde España 932 415 960
Llamadas desde fuera de España +34 932 415 960
Bibliografía
[1]
E. Martínez-Vila, M. Murie Fernández, I. Pagola, P. Irimia.
Enfermedades cerebrovasculares.
Medicine, (2011), 10 pp. 4871-4881
[2]
Acuerdo para el uso del término ICTUS. Guía para el diagnóstico y tratamiento del ictus. Guías oficiales de la Sociedad Española de Neurología, Prous Science,
[3]
2019030206210795310
J.C. Hemphill 3rd, S.M. Greenberg, C.S. Anderson, K. Becker, B.R. Bendok, M. Cushman, American Heart Association Stroke Council; Council on Cardiovascular and Stroke Nursing; Council on Clinical Cardiology, et al.
Guidelines for the Management of spontaneous intracerebral hemorrhage: a guideline for healthcare professionals from the American Heart Association/American Stroke Association.
Stroke, (2015), 46 pp. 2032-2060
[4]
2019030206210795311
M. Rodríguez Yánez, M. Castellanos, M.M. Freijo, J.C. López Fernández, J. Martí-Fàbregas, F. Nombela, et al.
Guías de actuación clínica en la hemorragia intracerebral.
Neurología, (2013), 28 pp. 236-249
[5]
C.J. Van Asch, M.J. Luitse, G.J. Rinkel, I. van der Tweel, A. Algra, C.J. Klijn.
Incidence, case fatality, and functional outcome of intracerebral haemorrhage over time, according to age, sex, and ethnic origin: a systematic review and meta-analysis.
Lancet Neurol., (2009), 9 pp. 167-176
[6]
M. Giroud, P. Gras, N. Chadan, P. Beuriat, C. Milan, P. Arveux, et al.
Cerebral haemorrhage in a French prospective population study.
J Neurol Neurosurg Psychiatry, (1991), 54 pp. 595-598
[7]
C.J. Counsell, S. Boonyakarnkul, M. Dennis, P. Sandercock, J. Bamford, J. Burn, et al.
Primary intracerebral haemorrhage in the Oxfordshire Community Stroke Project, 2: prognosis.
Cerebrovasc Dis, (1995), 5 pp. 26-34
[8]
T. Brott, K. Thalinger, V. Hertzberg.
Hypertension as a risk factor for spontaneous intracerebral hemorrhage.
Stroke, (1986), 17 pp. 1078-1083
[9]
A. Viswanathan, S.M. Greenberg.
Intracerebral hemorrhage.
Handbook of clinical neurology. Stroke. Part II: Clinical manifestations and pathogenesis, Elsevier B.V., pp. 767-790
[10]
2019030206210795312
2019030206210795313
A.I. Qureshi, A.D. Mendelow, D.F. Hanley.
Intracerebral haemorrhage.
Lancet, (2009), 373 pp. 1632-1644
[11]
M.J. O’Donnel l, D. Xavier, L. Liu, H. Zhang, S.L. Chin, P. Rao-Melacini, et al.
Risk factors for ischemic and haemorrhagic stroke in 22 countries (the INTERSTROKE study): a case control study.
[12]
P. Irimia-Sieira, M. Moya, E. Martínez-Vila.
Clinical aspects and prognostic factors of intracerebral hemorrhage.
Rev Neurol., (2000), 31 pp. 192-198
[13]
S. Passero, R. Rocchi, S. Rossi, M. Ulivelli, G. Vatti.
Seizures after spontaneous supratentorial intracerebral hemorrhage.
Epilepsia, (2002), 43 pp. 1175-1180
[14]
S. Runchey, S. McGee.
Does this patient have a hemorrhagic stroke?.: clinical findings distinguishing hemorrhagic stroke from ischemic stroke.
JAMA, (2010), 303 pp. 2280-2286
[15]
P. Irimia, S. Asenbaum, M. Brainin, H. Chabriat, E. Martínez-Vila, K. Niederkorn, et al.
Use of imaging in cerebrovascular disease.
European handbook of neurological management, Blackwell Publishing Ltd, pp. 19-34
[16]
2019030206210795314
2019030206210795315
R. Wada, R.I. Aviv, A.J. Fox, D.J. Sahlas, D.J. Gladstone, G. Tomlinson, et al.
CT angiography «spot sign» predicts hematoma expansion in acute intracerebral hemorrhage.
[17]
A. Charidimou, Farid, J.C. Baron.
Amyloid-PET in sporadic cerebral amyloid angiopathy: A diagnostic accuracy meta-analysis.
Neurology, (2017), 89 pp. 1490-1498
[18]
B. Fuentes, J. Castillo, B. San José, R. Leira, J. Serena, V. Vivancos, et al.
The prognostic value of capillary glucose levels in acute stroke: the GLycemia in Acute Stroke (GLIAS) study.
[19]
C.S. Anderson, Y. Huang, H. Arima, E. Heeley, C. Skulina, M.W. Parsons, et al.
Effects of early intensive blood pressure lowering treatment on the growth of hematoma and perihematomal edema in acute intracerebral hemorrhage: the Intensive Blood Pressure Reduction in Acute Cerebral Haemorrhage Trial (INTERACT).
[20]
C.K. Dastur, W. Yu.
Current management of spontaneous intracerebral haemorrhage.
Stroke Vasc Neurol., (2017), 2 pp. e000047
[21]
2019030206210795316
2019030206210795317
N. Sprigg, K. Flaherty, J.P. Appleton, R. Al-Shahi Salman, D. Bereczki, M. Beridze, et al.
Tranexamic acid for hyperacute primary IntraCerebral Haemorrhage (TICH-2): an international randomised, placebo-controlled, phase 3 superiority trial.
Lancet, (2018), 391 pp. 2107-2115
[22]
2019030206210795318
S.A. Mayer, S.M. Davis, B.E. Skolnick, N.C. Brun, K. Begtrup, J.P. Broderick, et al.
Can a subset of intracerebral hemorrhage patients benefit from hemostatic therapy with recombinant activated factor VII?.
[23]
J. Martí Fàbregas, R. Belvís, E. Guardia, D. Cocho, J. Muñoz, L. Marruecos, et al.
Prognostic value of Pulsatility Index in acute intracerebral hemorrhage.
Neurology, (2003), 61 pp. 1051-1056
[24]
A.D. Mendelow, B.A. Gregson, H.M. Fernandes, G.D. Murray, G.M. Teasdale, D.T. Hope, et al.
Early surgery versus initial conservative treatment in patients with spontaneous supratentorial intracerebral haematomas in the International Surgical Trial in Intracerebral Haemorrhage (STICH): a randomised trial.
[25]
2019030206210795319
2019030206210795320
C.J. Chen, D. Ding, T.J. Buell, F.D. Testai, S. Koch, D. Woo, et al.
Restarting antiplatelet therapy after spontaneous intracerebral hemorrhage. Functional outcomes.
Neurology, (2018), 91 pp. e26-e36
[26]
Z. Zhou, J. Yu, C. Carcel, C. Delcourt, J. Shan, R.I. Lindley, et al.
Resuming anticoagulants after anticoagulation-associated intracranial haemorrhage: systematic review and meta-analysis.
BMJ Open, (2018), 8 pp. e019672