

Vol. 12. Núm. 17.
Páginas 995-999 (Septiembre 2016)

Protocolos de práctica asistencial
Protocolo de evaluación y tratamiento de la disfunción sexual en el varón con diabetes

Assessment and treatment protocol for sexual dysfunction in male patients with diabetes

L. Bassas Arnau
Doi : https://10.1016/j.med.2016.09.008
Opciones
Resumen
Epidemiología

La disfunción eréctil es frecuente en hombres diabéticos, y se relaciona con el tiempo de evolución de la diabetes, la edad y las complicaciones vasculares y neurológicas.

Etiopatogenia

Las lesiones arteriales, la neuropatía autonómica y la disfunción del endotelio se combinan en la producción de disfunción eréctil.

Evaluación diagnóstica

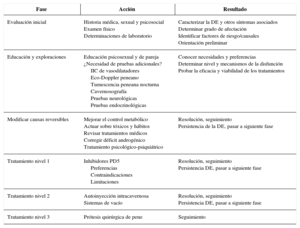
Se basa en caracterizar los síntomas, definir el contexto psicosexual del paciente, identificar los factores de riesgo y atender a las necesidades particulares. La objetivación de la erección tras la inyección intracavernosa de fármacos vasodilatadores, asociada al eco-Doppler son pruebas diagnósticas útiles para comprobar los mecanismos alterados.

Tratamiento

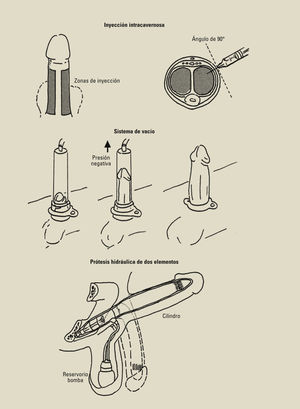
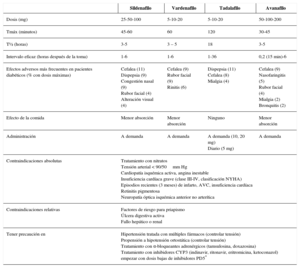
La primera línea de tratamiento la forman los inhibidores específicos de la fosfodiesterasa tipo 5. Se puede inducir la erección con inyección intracavernosa o intrauretral de vasodilatadores. Los sistemas de vacío no requieren inyección ni fármacos. Las prótesis de pene se pueden implantar quirúrgicamente en el interior de los cuerpos cavernosos en los casos resistentes a otros tratamientos.

Palabras clave
Diabetes mellitus
Disfunción eréctil
Disfunción sexual
Testosterona
Inhibidores de la fosfodiesterasa 5
Alprostadil
Prótesis de pene
Abstract
Epidemiology

Erectile dysfunction is common among diabetic men, and is related to the duration of diabetes, age and vascular and neurological complications.

Etiopathogenesis

The production of erectile dysfunction arises from combined effects of endothelial dysfunction, arterial damage and autonomic neuropathy.

Diagnostic assessment

It is based on the profile of the symptoms, the definition of the psychosocial context of the patient, the identification of risk factors and the knowledge of individual needs. The objective measurement of erectile response after intracavernous injection of vasodilators plus Doppler ultrasound are useful diagnostic tests to check the mechanisms involved.

Treatment

The first line of treatment are the specific inhibitors of phosphodiesterase type 5. Erections can be induced by vasodilator drugs administered intracavernous or intraurethral. Vacuum constriction devices do not require either drugs or injections. Surgical penile prostheses may be implanted into the carvernous corpora when other treatments are not effective.

Keywords
Diabetes mellitus
Erectile dysfunction
Sexual dysfunction
Testosterone
Phosphodiesterase 5 inhibitors
Alprostadil
Penile prosthesis

Identifíquese

¿Aún no es suscriptor de la revista?

Comprar el acceso al artículo

Comprando el artículo el pdf del mismo podrá ser descargado

Teléfono para incidencias

De lunes a viernes de 9h a 18h (GMT+1) excepto los meses de julio y agosto que será de 9 a 15h

Llamadas desde España 932 415 960
Llamadas desde fuera de España +34 932 415 960
Bibliografía
[1]
201611050031173798
201611050031173799
A.E. Weinberg, M. Eisenberg, C.J. Patel, G.M. Chertow, J.T. Leppert.
Diabetes severity, metabolic syndrome, and the risk of erectile dysfunction.
J Sex Med., (2013), 10 pp. 3102-3109
[2]
2016110500311737910
T.J. Bivalacqua, M.F. Usta, H.C. Champion, P.J. Kadowitz, W.J.G. Hellstrom.
Endothelial dysfunction in erectile dysfunction: role of the endothelium in erectile physiology and disease.
J Androl., (2003), 24 pp. S17-S37
[3]
2016110500311737911
G. Corona, M. Monami, G. Rastrelli, A. Aversa, A. Sforza, A. Lenzi, et al.
Type 2 diabetes mellitus and testosterone: a meta-analysis study.
Int J Androl., (2011), 34 pp. 528-540
[4]
2016110500311737912
E.J. Tejero, R.V. Chicharro, E.V. Vargas, A.M. Morales.
Historia clínica dirigida y exploración física en pacientes con disfunción eréctil: aspectos clínicos que no podemos olvidar.
Arch Esp Urol., (2010), 63 pp. 679-686
[5]
2016110500311737913
2016110500311737914
M. Khera, I. Goldstein.
Erectile dysfunction.
BMJ Clin Evid., (2011), 2011
pii: 1803
[6]
2016110500311737915
M.A. Vickers, E.A. Wright.
Erectile dysfunction in the patient with diabetes mellitus.
Am J Manag Care., (2004), 10 pp. S3-S11
[7]
2016110500311737916
I. Goldstein, L.A. Jones, L.H. Belkoff, G.S. Karlin, C.H. Bowden, C.A. Peterson, et al.
Avanafil for the treatment of erectile dysfunction: a multicenter, randomized, double-blind study in men with diabetes mellitus.
Mayo Clin Proc., (2012), 87 pp. 843-852
[8]
2016110500311737917
M.R. Pinsky, A. Chawla, W.J. Hellstrom.
Tratamiento intracavernoso y dispositivos de vacío en el tratamiento de la disfunción eréctil.
Arch Esp Urol., (2010), 63 pp. 717-725
[9]
2016110500311737918
S. Lee, J. Lee, Y.W. Choi.
Design and evaluation of prostaglandin E1 (PGE1) intraurethral liquid formulation employing self-microemulsifying drug delivery system (SMEDDS) for erectile dysfunction treatment.
Biol Pharm Bull., (2008), 31 pp. 668-672
[10]
2016110500311737919
G. Garaffa, C. Li, I. Moncada, D.J. Ralph.
Surgical management of erectile dysfunction.
Arch Esp Urol., (2010), 63 pp. 728-738